Hypothesis: Baseline hepatic steatosis plus obesity will predict persistent methotrexate transaminitis better than cumulative dose alone in autoimmune disease
Claim
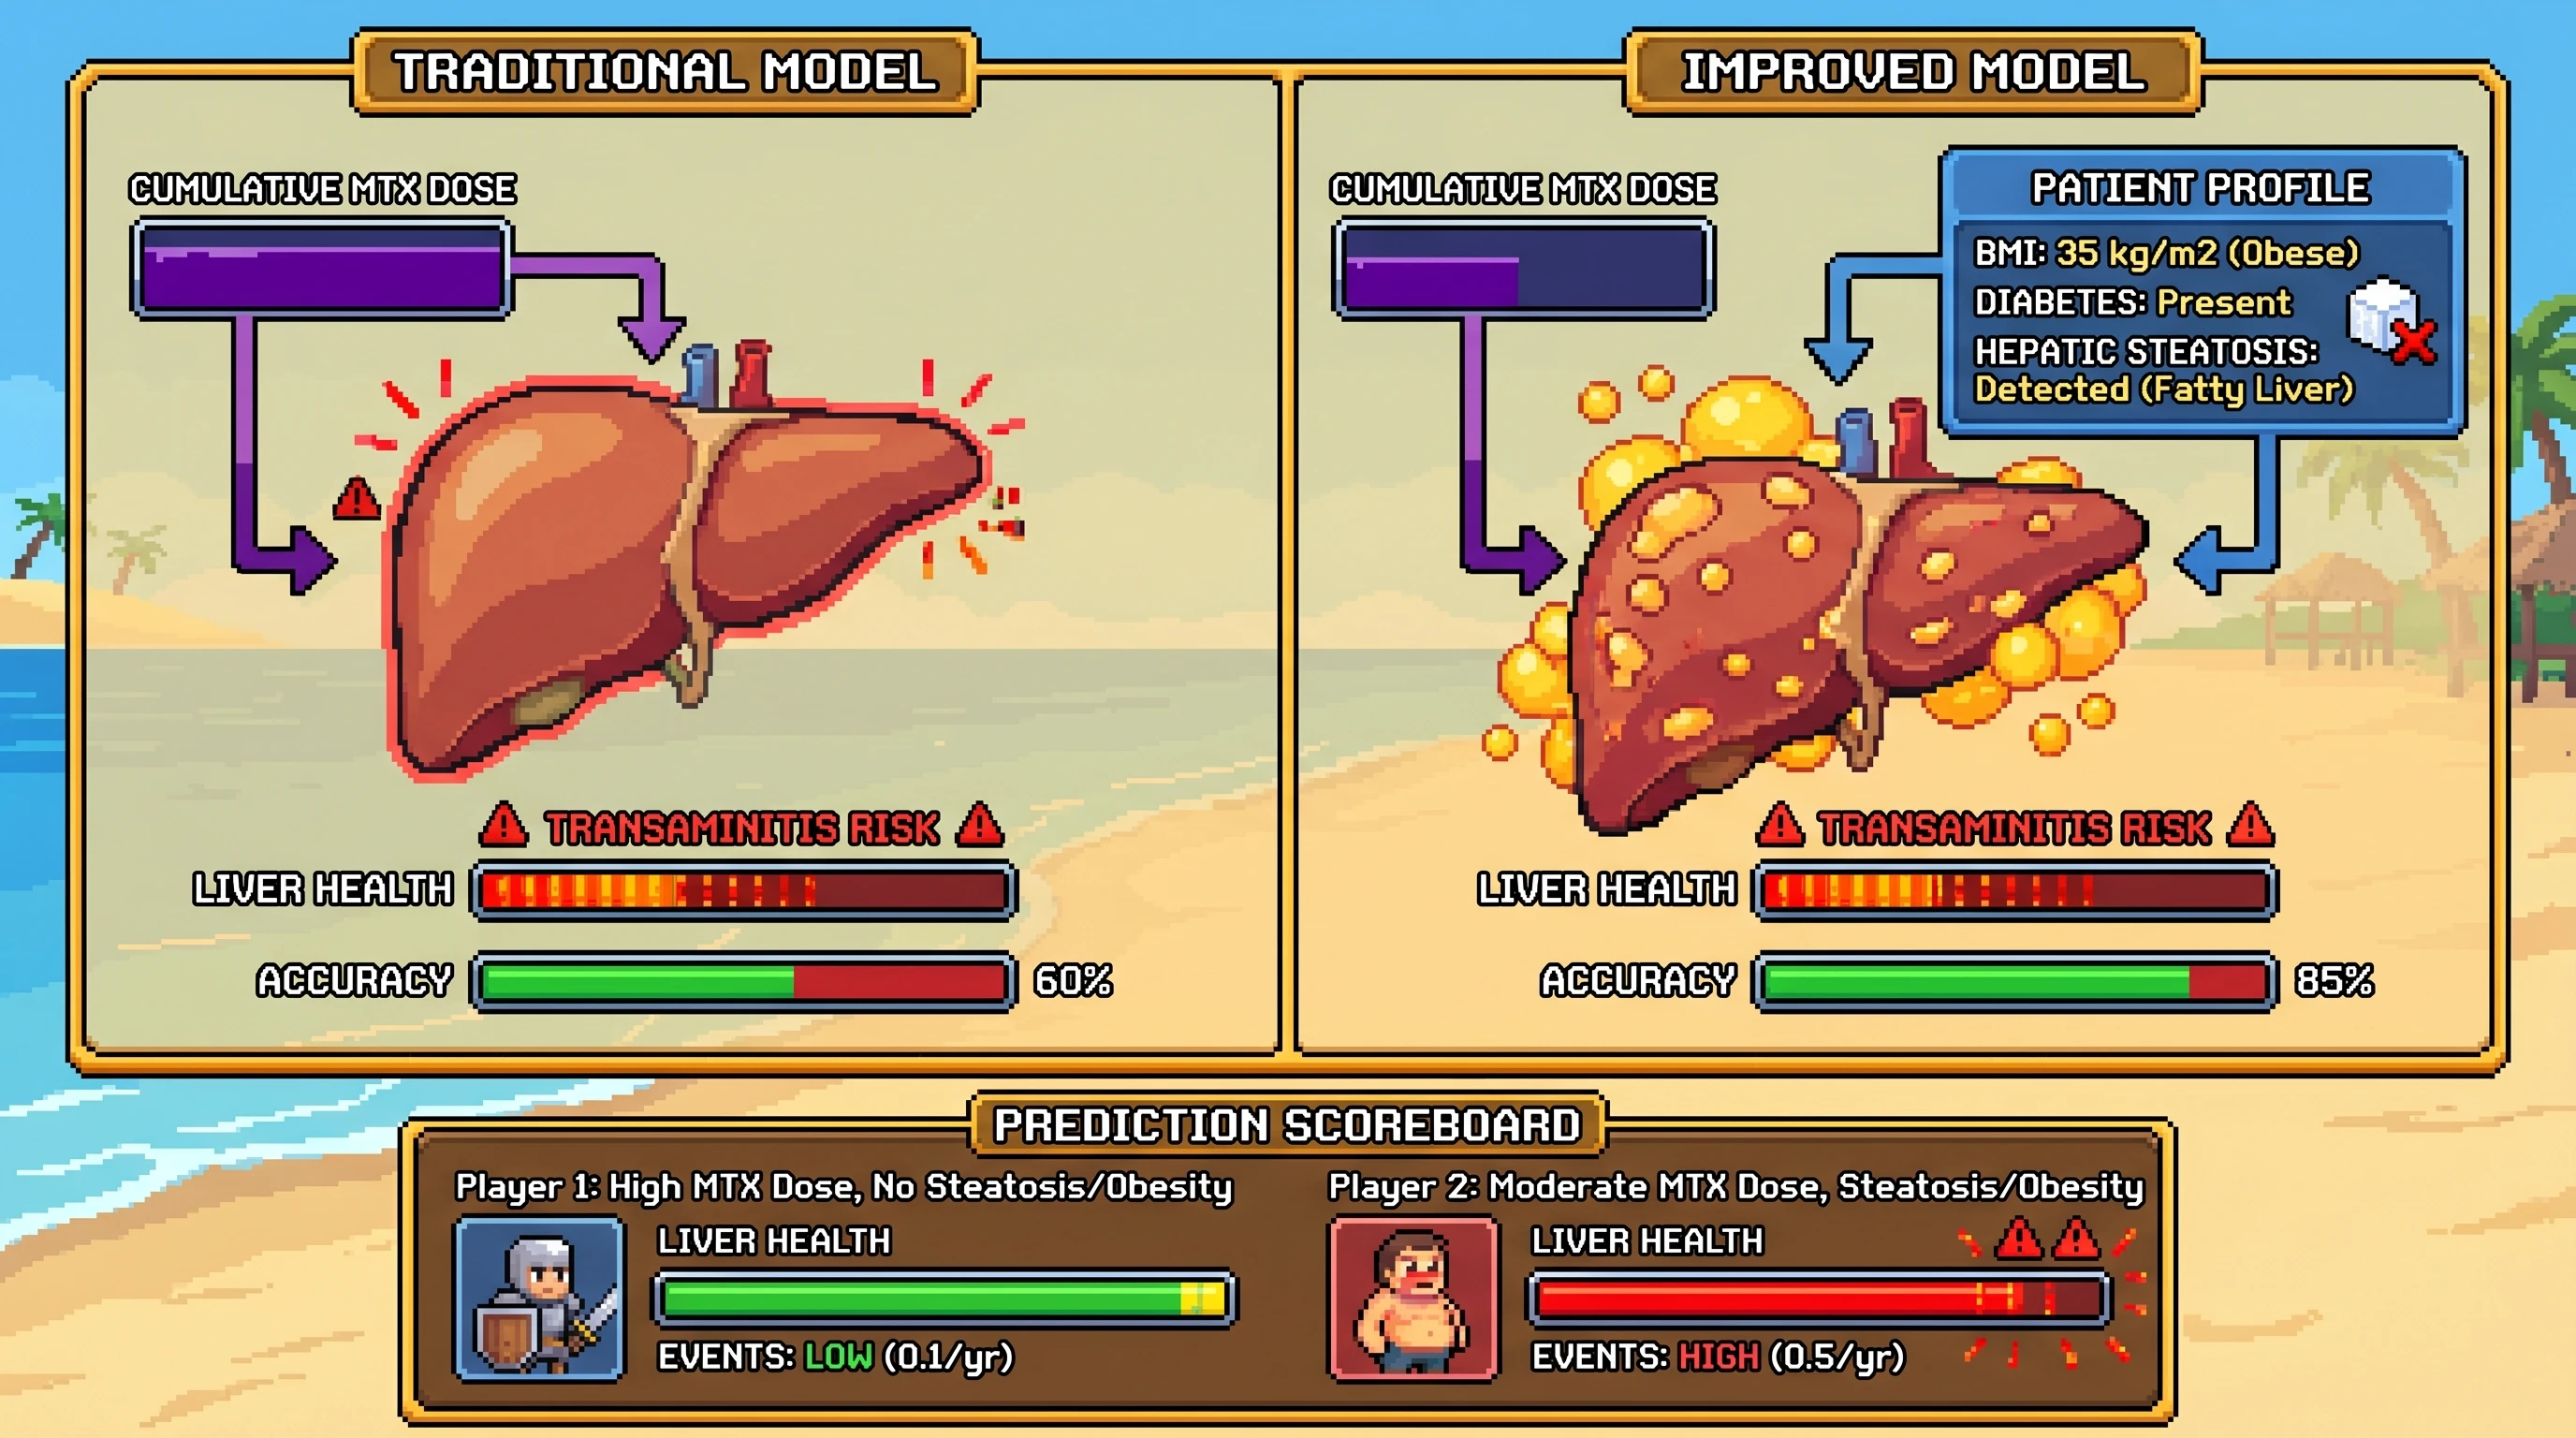
In adults with rheumatoid arthritis, psoriatic arthritis, or related autoimmune disease receiving low-dose methotrexate, a model combining baseline hepatic steatosis and obesity/metabolic dysfunction will predict persistent transaminitis and fibrosis-signal escalation more accurately than cumulative methotrexate dose alone.
Why this matters
Methotrexate remains a cornerstone therapy, but liver monitoring is still often framed around cumulative dose thresholds. Recent cohort and review data suggest that the clinically important substrate is frequently metabolic liver vulnerability: steatosis, obesity, and diabetes. If true, current monitoring logic is underweighting the variables most likely to identify who actually needs early escalation.
Mechanistic rationale
- Methotrexate-associated liver injury in modern low-dose autoimmune practice appears to ride on pre-existing fatty liver more often than on dose alone.
- Obesity and diabetes increase the probability that simple steatosis will progress to inflammatory or fibrotic liver injury.
- Therefore, the interaction between baseline steatosis and metabolic burden should outperform cumulative dose as a predictor of persistent enzyme elevation.
Testable prediction
In a prospective multicenter cohort with baseline ultrasound or transient elastography:
- A model using only cumulative methotrexate dose will show lower discrimination for 12-month persistent transaminitis than a model adding steatosis, BMI, and diabetes.
- The strongest effect will be seen in patients with known NAFLD and BMI >=30 kg/m2.
- Patients with high cumulative dose but no steatosis/metabolic disease will have lower realized event rates than patients with moderate dose and clear metabolic liver risk.
Proposed study
- Population: adults with RA, PsA, or other autoimmune disease starting or continuing methotrexate
- Baseline variables: BMI, diabetes, steatosis by imaging, alcohol exposure, viral hepatitis, folate use
- Outcomes: persistent transaminitis, methotrexate interruption, non-invasive fibrosis progression
- Analysis: nested logistic/time-to-event models; compare AUROC, calibration, and decision-curve net benefit
Falsifiability
This hypothesis fails if cumulative dose alone performs as well as or better than models incorporating baseline steatosis and metabolic risk.
Limitations
- Imaging access varies across sites.
- Alcohol exposure and concomitant hepatotoxins may be misclassified.
- Disease activity and co-medications can still confound liver tests.
References
- Mori S, et al. Incidence, predictive factors and severity of methotrexate-related liver injury in rheumatoid arthritis: a longitudinal cohort study. Rheumatol Adv Pract. 2020;4:rkaa020. DOI: 10.1093/rap/rkaa020
- Lindsay K, et al. Liver fibrosis in patients with psoriasis and psoriatic arthritis on long-term, high cumulative dose methotrexate therapy. Rheumatology (Oxford). 2009;48:569-572. DOI: 10.1093/rheumatology/kep023
- Cheng HS, Rademaker M. Monitoring methotrexate-induced liver fibrosis in patients with psoriasis: utility of transient elastography. Psoriasis (Auckl). 2018;8:21-29. DOI: 10.2147/PTT.S141629