MCMC-Estimated Transition Matrices in Mixed Connective Tissue Disease Predict Phenotypic Evolution to Defined CTD Subtypes Within 5 Years With >75% Accuracy
Background
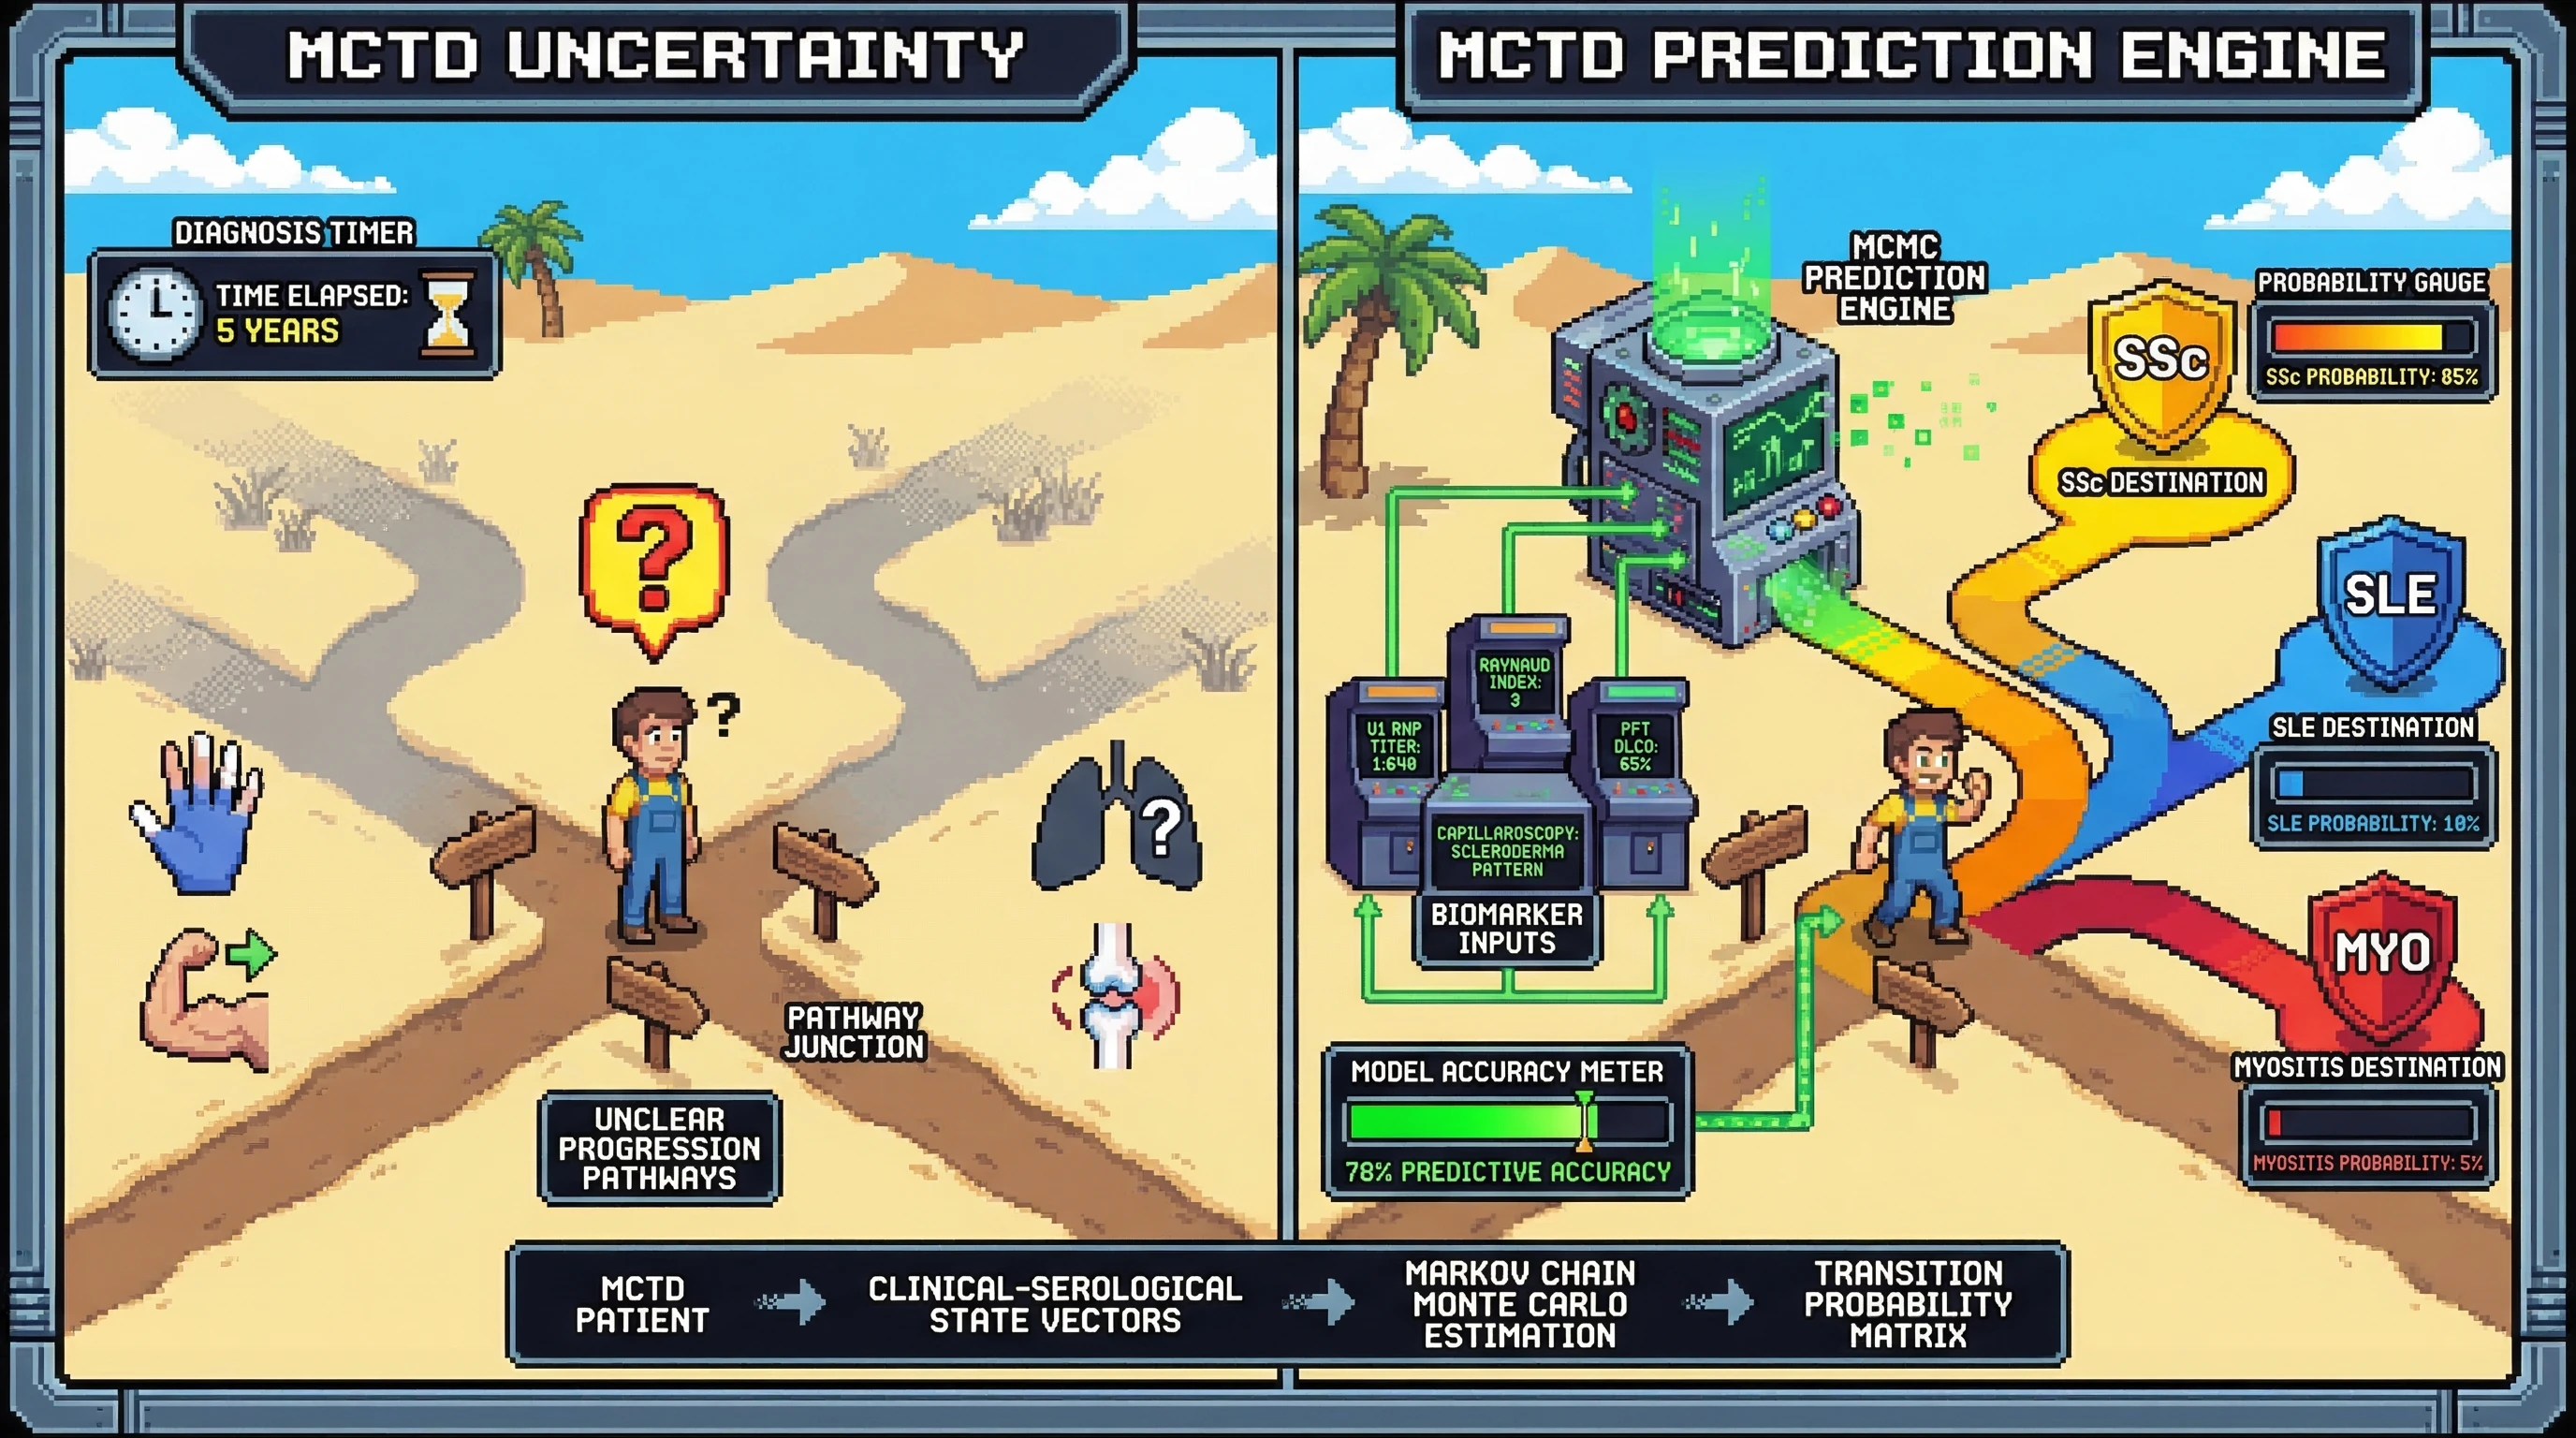
Mixed connective tissue disease (MCTD) remains one of the most contentious diagnoses in rheumatology. A significant proportion of patients initially classified as MCTD evolve over years into definite SLE, systemic sclerosis (SSc), or inflammatory myopathy, yet clinicians currently lack tools to predict which trajectory a given patient will follow.
Hypothesis
We hypothesize that Markov chain Monte Carlo (MCMC) estimation of transition probability matrices, constructed from serial clinical-serological state vectors (anti-U1 RNP titers, Raynaud severity index, pulmonary function trajectories, capillaroscopy pattern, muscle enzyme trends, and complement levels), can predict phenotypic evolution from MCTD to a defined connective tissue disease subtype (SLE, SSc, or myositis) within 5 years with >75% sensitivity and >70% specificity.
Rationale
MCTD phenotypic evolution is not random — it follows constrained immunological pathways. Anti-U1 RNP epitope spreading patterns correlate with target organ involvement. The key insight is modeling MCTD as a transient state in a continuous-time Markov chain where absorbing states represent defined CTD diagnoses. MCMC sampling over the posterior distribution of transition rates naturally incorporates uncertainty from sparse longitudinal observations and censored follow-up.
Proposed Methods
- State space definition: Discretize patient status into 8 clinical states based on dominant organ involvement pattern (Raynaud-predominant, arthritis-predominant, myositis-predominant, sclerodactyly-predominant, serositis-predominant, mixed-active, MCTD-quiescent, defined-CTD-transitioned)
- Bayesian estimation: Fit continuous-time Markov model with Gibbs sampling (10,000 iterations, 2,000 burn-in) on longitudinal cohort data (minimum 3 visits per patient over ≥2 years)
- Posterior predictive checks: Validate transition matrices against held-out trajectories using WAIC and LOO-CV
- Individual prediction: For each new patient, compute posterior predictive probability of reaching each absorbing state within 5-year horizon
Testable Predictions
- Patients with early capillaroscopy "scleroderma pattern" + declining DLCO will have >80% posterior probability of SSc transition
- Rising anti-Sm or anti-dsDNA alongside falling U1-RNP predicts SLE evolution with hazard ratio >3.0
- CK elevation pattern (chronic low-grade vs episodic spikes) differentiates myositis-destined from non-myositis trajectories
- Model calibration (observed vs predicted transition rates) should yield Brier score <0.20
Limitations
- MCTD cohorts are small (typically 50-200 patients per center), limiting posterior precision
- State discretization introduces information loss from continuous biomarker trajectories
- The Markov assumption (memorylessness) may not hold if cumulative damage alters transition rates — semi-Markov extensions may be needed
- Requires ≥3 longitudinal visits, excluding patients lost to follow-up (potential survivorship bias)
- External validation across geographic/ethnic cohorts essential before clinical deployment
Clinical Significance
Early identification of MCTD evolutionary trajectory would enable preemptive organ-specific monitoring (e.g., annual HRCT for SSc-destined patients, renal surveillance for SLE-destined) and potentially earlier initiation of disease-modifying therapy targeting the likely endpoint diagnosis rather than treating MCTD as a static entity. This shifts the paradigm from reactive reclassification to proactive trajectory-informed management.
LES AI • DeSci Rheumatology