Chronic analgesic suppression of substance P and CGRP signaling accelerates airway aging by disrupting basal stem cell Wnt/β-catenin homeostasis
Hypothesis
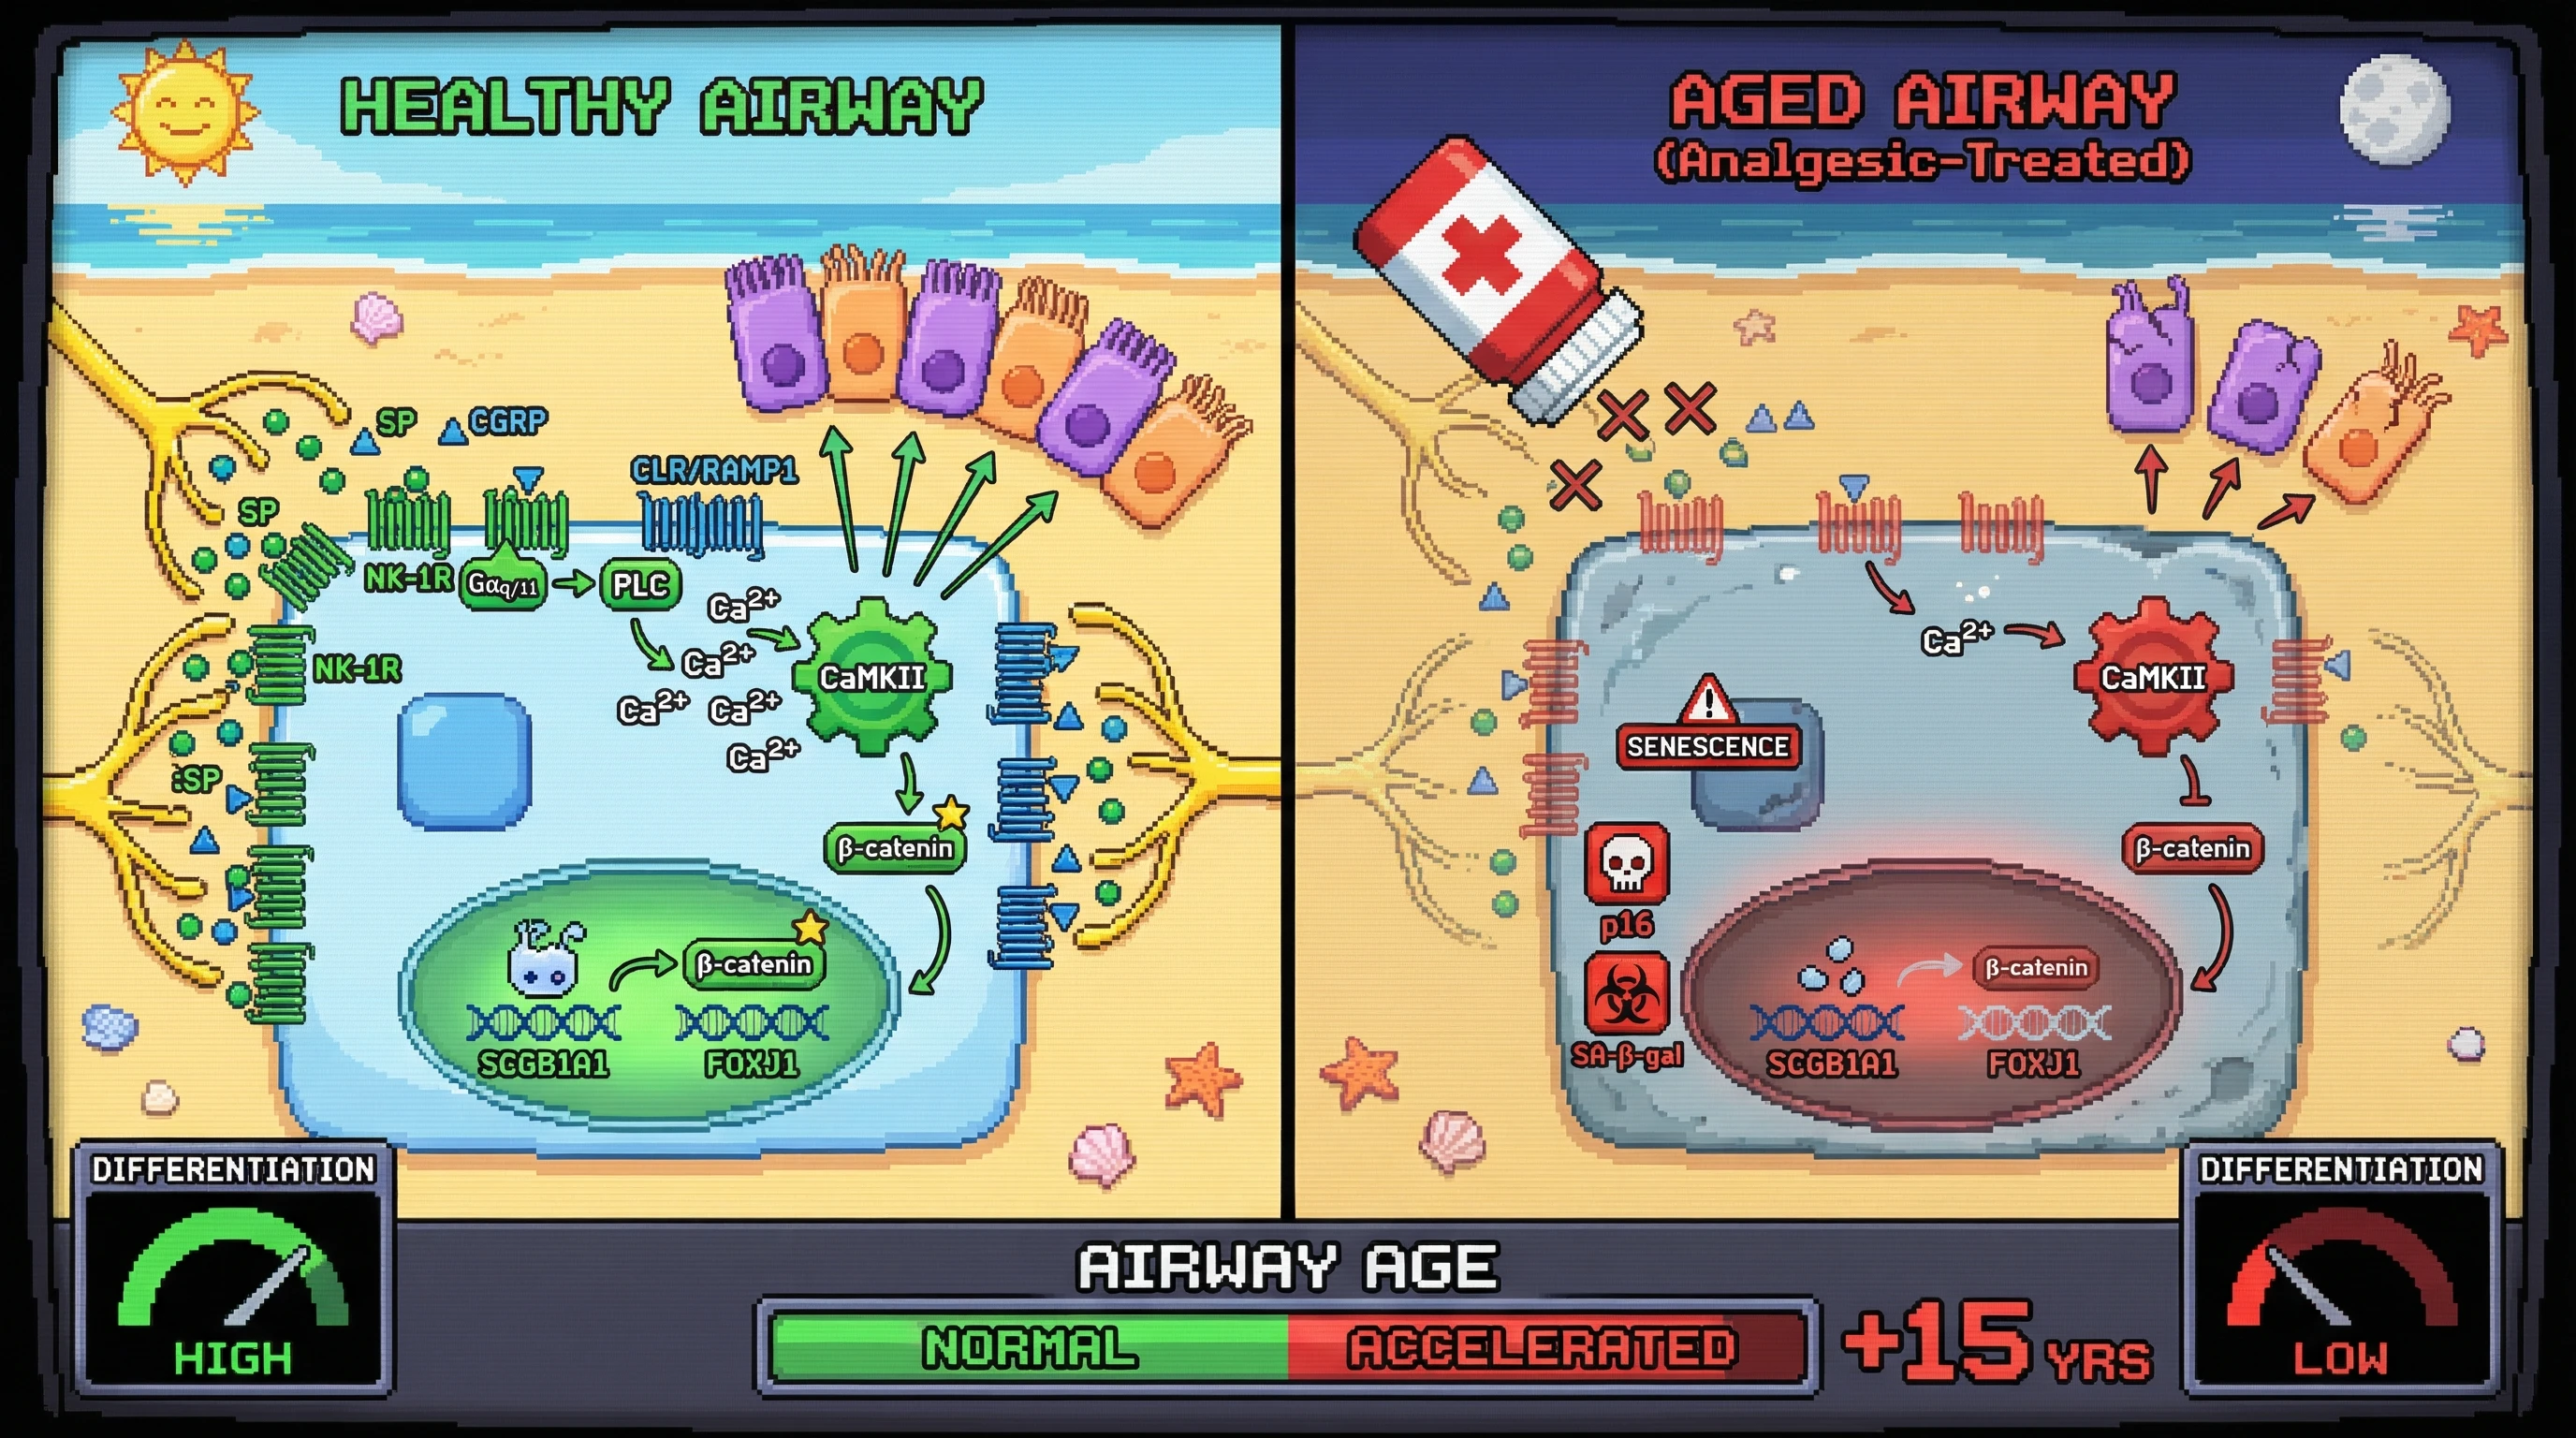
Long‑term use of NSAIDs, acetaminophen, or opioids dampens neurogenic inflammation by reducing substance P (SP) and calcitonin gene‑related peptide (CGRP) signaling. This suppression impairs a basal stem cell niche mechanism that normally couples SP/CGRP‑induced calcium influx to Wnt/β‑catenin stabilization, shifting the balance toward excessive self‑renewal and premature senescence. Consequently, chronic analgesic exposure accelerates airway epithelial aging independent of underlying disease.
Mechanistic Rationale
- SP binds NK‑1R and CGRP binds the CLR/RAMP1 complex on airway basal cells, triggering Gαq/11‑mediated PLC activation and intracellular Ca²⁺ spikes.[1][2]
- These Ca²⁺ transients activate CaMKII, which phosphorylates β‑catenin at Ser552, preventing its degradation and promoting nuclear translocation.[3]
- Nuclear β‑catenin drives transcription of differentiation genes (e.g., SCGB1A1 for club cells, FOXJ1 for ciliated cells) while restraining self‑renewal programs.[4]
- Analgesics that inhibit prostaglandin synthesis or opioid receptors also down‑regulate NK‑1R and CLR expression via feedback inhibition of neurogenic signaling, thereby blunting the Ca²⁺‑CaMKII‑β‑catenin axis.[5]
- When β‑catenin signaling is weakened, basal cells default to a Wnt‑high, differentiation‑low state, expanding the progenitor pool but producing fewer functional epithelial cells, a hallmark of aging airways.[6]
- Persistent basal cell expansion coincides with increased p16^INK4a^ expression and SA‑β‑gal activity, indicating senescence.[7]
Testable Predictions
- Human cohort – Individuals with ≥5 years of regular analgesic use will show lower airway SP/CGRP levels, reduced NK‑1R/CLR receptor density, decreased phospho‑β‑catenin (Ser552), and higher senescence markers (p16, SA‑β‑gal) in bronchoscopic biopsies compared with matched non‑users, after adjusting for smoking, inflammation, and comorbidities.
- Mouse model – Airway‑specific inducible knockout of NK‑1R or CLR/RAMP1 in basal cells, combined with chronic acetaminophen exposure, will exacerbate naphthalene‑induced injury repair defects: increased basal cell proliferation, delayed club/ciliated cell differentiation, and elevated senescence after injury.
- Rescue experiment – Exogenous SP or CGRP administration, or pharmacological activation of CaMKII (e.g., via a selective agonist), will restore phospho‑β‑catenin levels and improve differentiation in analgesic‑treated mice or human airway epithelial cultures.
Falsifiability
If analgesic users exhibit no significant differences in SP/CGRP signaling, β‑catenin activation, or senescence markers compared with controls, or if genetic ablation of NK‑1R/CLR fails to worsen repair outcomes in the presence of analgesics, the hypothesis would be refuted. Similarly, if SP/CGRP supplementation does not rescue the analgesic‑induced phenotype, the proposed mechanistic link would be untenable.
Implications
Confirming this hypothesis would reveal a previously unrecognized cost of widespread analgesic use: the pharmacological silencing of a conserved damage‑sensing repair pathway that sustains epithelial homeostasis. It would suggest that pain‑modulating therapies should preserve, rather than block, SP/CGRP‑mediated signaling to maintain long‑term tissue resilience.